
Overview – Chaney et al (2004)
Chaney et al (2004) investigated whether a new asthma device called the Funhaler could improve children’s adherence to their prescribed asthma medication. The Funhaler included incentive toys – such as a spinner and whistle – which were designed to make using the device more fun and encourage children to use the correct breathing technique. The study compared the Funhaler with a standard inhaler and the researchers found that children were more likely to receive their medication as recommended when using the Funhaler. The study was based on the principles of operant conditioning, which suggests that behaviour can be strengthened by positive reinforcement (in this case the fun and rewarding features of the Funhaler).
You can jump to different sections of this article via the links below:
- Aim
- Method (sampling and procedure)
- Results
- Conclusions
- Evaluation and methodological issues
- Relation to other core developmental psychology studies
Chaney et al (2004)
Aim
The main aim of the study was to investigate whether using the Funhaler would improve children’s adherence to their prescribed asthma medication.
 The study was based on operant conditioning, which is a form of learning in which behaviour is influenced by its consequences. Behaviour that is followed by a desirable consequence is more likely to be repeated. For example, if a child is given praise for taking their asthma medication, they may be more likely to take it again in the future.
The researchers were interested in applying this principle to asthma treatment. Poor adherence – i.e. not following a prescribed treatment correctly or regularly – is a common problem among children with asthma. Previous research had found that only around 30% to 70% of children regularly received their medication as prescribed. Correct use of a pressurised metered dose inhaler (pMDI) was also low.
The researchers thus wanted to investigate whether making the process of using an inhaler more enjoyable could encourage children to use it more effectively.
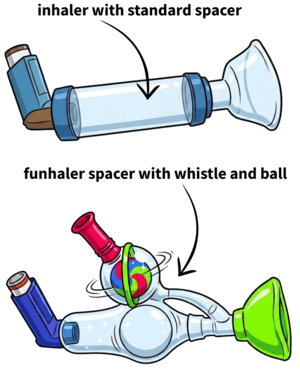
The Funhaler was designed to provide positive reinforcement. It contained incentive toys, such as a spinner and whistle, which were designed to make using the inhaler more fun. The toys were also designed to encourage the deep breathing needed for effective medication delivery.
Overall, the study was designed to investigate whether principles of operant conditioning could be applied to improve children’s health behaviour.
Method
Chaney et al used a field experiment (children used the inhalers in their normal home environment rather than a laboratory setting) with a repeated measures design (i.e. the same participants used a regular inhaler and used the Funhaler and the results were compared).
The independent variable (IV) was the type of inhaler used:
- Standard inhaler: used the Breath-a-Tech small-volume spacer.
- Funhaler: used a new spacer containing incentive toys.
The dependent variable (DV) was the children’s adherence to their prescribed asthma treatment. Adherence meant how consistently and correctly the children followed the prescribed medication regime.
The researchers collected data using parent questionnaires. Parents completed questionnaires before and after using the Funhaler.
Participants and sampling
The researchers used an opportunity sample, as they recruited children with asthma who were readily available and had already been prescribed a pressurised metered dose inhaler (pMDI) and spacer.
The characteristics of the participants were as follows:
- 32 children
- 22 boys and 10 girls
- Aged between 1.5 and 6 years (mean and median age ~3.2 years)
- Average duration of asthma of approximately 2.2 years
Parents provided informed consent and also helped their children use the inhalers where necessary.
Procedure
The study took place in the children’s homes.
Before
Before the Funhaler was introduced, parents were asked about their existing use of the standard inhaler. The researchers used questionnaires to collect information about:
- How easy the standard device was to use
- How successfully parents could medicate their children
- How regularly the children received their medication
- Attitudes towards the treatment.
During
Then the children were then given the Funhaler to use for 2 weeks.
The Funhaler contained incentive toys, such as a spinner and whistle. The toys were designed to encourage the child to take deep breaths. This was intended to make the correct inhalation technique more enjoyable and rewarding. The modular design also meant that different incentive toys could potentially be used if children became bored with a particular toy.
The toys were placed in a separate branch of the device so that they did not interfere with the main drug-delivery circuit. The researchers also compared the Funhaler’s aerosol output with the standard inhaler that used a Breath-a-Tech spacer. The two devices were similar in size (Breath-a-Tech: 235 ml, Funhaler: 225 ml) and so the Funhaler did not compromise the delivery of the medication.
The researchers contacted parents by telephone at a random date during the 2-week period of using the Funhaler and asked whether they had attempted to give their child asthma medication on the previous day.
After
After the 2-week period, the children had used both the standard inhaler and the Funhaler. The researchers then asked the parents to complete questionnaires and interviewed them about their experiences with the two devices.
The researchers collected both quantitative information about adherence and more detailed qualitative information about parents’ experiences of using the two devices.
Results
The results showed that the use of the Funhaler was associated with improved adherence by both children and parents.
The researchers compared the Funhaler with the standard inhaler on several measures, such as whether children received their medication, whether they used the recommended breathing technique, and whether parents could successfully administer the medication.
The table below shows the main measures of adherence:
| Normal device | Funhaler | |
|---|---|---|
| Children who had used their inhaler the day before (asked at a random interval) | 59% | 81% |
| Children who achieved four or more breath cycles per delivery | 50% | 80% |
| Parents successfully medicating child always | 10% | 73% |
When researchers contacted parents at random, 81% (22/27) of children using the Funhaler had received their medication on the previous day. This compared with 59% (16/27) when children used the standard device.
The researchers also measured whether children used the recommended breathing technique. 80% (24/30) of children using the Funhaler completed four or more breathing cycles per aerosol delivery, compared with 50% (15/30) when using the standard device. This difference was statistically significant (p = 0.02).
The table also shows a large difference in parental success. Only 10% of parents (3/30) reported that they were always successful when using the standard device. This increased to 73% (22/30) when using the Funhaler. This difference was statistically significant (p ≤ 0.001).
The second table shows the problems that children experienced when using the two devices. The Funhaler was associated with fewer problems across all of the measures:
| Problem | Children having problem with existing inhaler | Children having problem with Funhaler |
|---|---|---|
| Unwilling to use the mask | 58% | 3% |
| Unwilling to breathe through the device at all | 61% | 7% |
| Breathes through the device, but not deeply | 68% | 19% |
| Unwilling to breathe for very long through the device | 61% | 13% |
| Struggles a little | 32% | 10% |
| Struggles a lot | 35% | 3% |
| Screams when device is brought close to face | 48% | 3% |
For example, 58% of children were unwilling to use the mask with the standard device, compared with only 3% with the Funhaler. Similarly, 61% were unwilling to breathe through the standard device at all, compared with 7% with the Funhaler.
The researchers also looked at parents who had initially struggled to administer the medication using the standard device. Of the parents who were initially unsuccessful:
- 17 became successful with time and practice.
- 11 remained unsuccessful.
- When these 11 parents changed to the Funhaler, 7 were immediately successful.
- 1 became successful with time.
- Only 3 continued to experience problems.
The researchers also collected data on the children’s attitudes towards the two devices:
| Child’s attitude to using their device | Children with attitude to existing inhaler | Children with attitude to Funhaler |
|---|---|---|
| Pleasure | 10% | 68% |
| Acceptance | 58% | 19% |
| No interest in device | 3% | 3% |
| Suspicion | 0% | 10% |
| Mild fear or dislike | 13% | 0% |
| Strong fear or dislike | 19% | 0% |
| Panic or phobia | 6% | 0% |
The Funhaler was associated with a more positive response. For example, 68% of children showed pleasure when using the Funhaler, compared with only 10% when using the standard device. Strong fear or dislike also fell from 19% with the standard device to 0% with the Funhaler.
And the questionnaires also asked about parent attitudes towards the two devices:
| Parent’s approach to medicating their child | Parents with attitude to existing inhaler | Parents with attitude to Funhaler |
|---|---|---|
| Completely happy | 10% | 61% |
| Confident | 32% | 16% |
| Acceptance | 39% | 19% |
| Mild concern | 7% | 3% |
| Strong concern | 13% | 0% |
| Dislike | 16% | 0% |
For example, 61% of parents were completely happy with the Funhaler, compared with 10% with the standard device. The proportion reporting dislike fell from 16% with the standard device to 0% with the Funhaler.
So, in short:
- Children were more likely to have received their medication when using the Funhaler.
- More children used the recommended breathing technique with the Funhaler.
- Parents were more successful in administering medication with the Funhaler.
- The Funhaler was associated with fewer problems for parents and children.
- The Funhaler did not appear to compromise drug delivery.
Conclusions
Overall, Chaney et al concluded that the Funhaler may improve children’s adherence to asthma treatment.
Operant conditioning
The Funhaler used incentive toys to make using the device more rewarding. This provided a positive consequence for using the inhaler and appeared to encourage better adherence. Children were more likely to receive their medication and to use the recommended breathing technique when using the Funhaler.
These results thus support the idea that operant conditioning can be used to change behaviour and improve adherence to medical regimes.
Future research and clinical applications
The researchers also concluded that the Funhaler did not appear to compromise drug delivery. This was important because a device that increased adherence would not be useful if it reduced the amount of medication reaching the child.
However, Chaney et al describe their research as pilot study – a small preliminary study designed to investigate whether an approach appears promising before larger research is carried out. It only included 32 children and covered a relatively short period of use (2 weeks). As such, the study was not strong enough on its own to show that the Funhaler should be widely used in asthma treatment. The study also only measured adherence rather than whether the Funhaler actually improved children’s long-term asthma control or health.
The researchers thus concluded that the Funhaler was a promising approach but that further research was needed with larger samples and longer follow-up periods before it could be concluded that it would lead to better clinical outcomes for children with asthma. For example, children might become less interested in the incentive toys over time, or the effects might be different in a larger and more varied group of children.
Evaluation
Research methods and techniques
Chaney et al used a field experiment with repeated measures design.
- Real-world setting: The children used the devices in their own homes. This means the study examined adherence in a situation similar to where asthma treatment would normally take place.
- Repeated measures: The same children used both types of inhaler. This meant that each child acted as their own comparison. Individual differences between children were therefore less likely to explain differences between the two conditions.
- Order effects: Because the children used the devices sequentially, their experience with the first device may have affected their behaviour with the second. For example, parents may have become more skilled at administering medication through practice between the two conditions.
- Small sample: Only 32 children took part. This makes it difficult to know whether the same results would be found in a much larger group of children with asthma.
Population and sampling
The study involved 32 young children with asthma.
- Relevant sample: All participants had asthma and had been prescribed medication using a pMDI and inhaler. This meant that the participants were directly relevant to the research question.
- Small sample: The study involved only 32 children. This limits how confidently the findings can be generalised to the wider population of children with asthma.
- Unequal sex distribution: The sample contained 22 boys but only 10 girls. This means that the study provides limited evidence about whether the Funhaler would work equally well for boys and girls.
- Limited age range: The children were aged between 1.5 and 6 years. The findings may not generalise to older children or adolescents with asthma.
Types of data
The study produced both quantitative and qualitative data.
- Quantitative data: Researchers recorded numerical measures of adherence and successful use of the devices.
- Easy to compare: Numerical data such as the percentage of children who had received their medication could be directly compared between the two devices.
- Statistical analysis: The researchers were able to test whether some differences between the devices were statistically significant.
- Qualitative information: Parents provided information about how easy the devices were to use, their attitudes towards treatment, and the problems they experienced.
- More detailed understanding: This information helped explain why the Funhaler might have improved adherence. It provided information about the experiences of parents and children that numerical measures alone could not show.
Representativeness and generalisability
The sample consisted of 32 young Australian children with asthma.
- Small sample: The small number of participants limits how confidently the findings can be generalised to all children with asthma.
- Limited age range: The participants were very young children. The findings may not apply to older children who may have different levels of independence when managing their asthma.
- Unequal numbers of boys and girls: There were more than twice as many boys as girls. This makes it difficult to know whether the findings apply equally to both sexes.
- Relevant participants: All of the children had asthma and were already prescribed medication using an inhaler. The sample was therefore appropriate for investigating the usefulness of a new asthma inhaler.
Ethical issues
- Informed consent: The children’s parents provided informed consent before their children took part in the study. This is important because the participants were very young and could not provide the same level of informed consent as adults.
- Protection from harm: The study involved children’s normal asthma treatment rather than deliberately exposing them to a harmful procedure. The Funhaler was also designed to deliver medication without compromising drug delivery.
- Children as participants: The participants were very young – including children as young as 1.5 years old. This means that researchers had an increased responsibility to ensure that the children were protected and that participation was appropriate.
- Medical treatment: The study was concerned with improving adherence to prescribed medication rather than withholding necessary treatment. This reduces some of the ethical concerns that could arise if children were deliberately denied treatment.
Validity
- Internal Validity: Are the findings caused by the experimental variables rather than another variable?
- Repeated measures: The same children used both devices. This reduced the effect of individual differences because the comparison was made within the same children.
- Demand characteristics: The parents may have guessed that the researchers expected the Funhaler to improve adherence because it was designed to be more fun for children. They may then have been more likely to encourage their child to use it or report positive results. This could reduce internal validity because some of the improvement may have resulted from the parents’ expectations rather than the Funhaler itself.
- Order effects: The children used the devices sequentially. Increased success with the Funhaler could partly reflect practice or increased familiarity with using an inhaler rather than the Funhaler itself.
- Self-report: Some measures of adherence were based on parents reporting whether medication had been given. Parents may have forgotten, misunderstood the question, or reported their behaviour inaccurately. This could reduce the accuracy of the measure.
- Ecological Validity: Do findings translate to the real world?
- Natural setting: The children used the devices in their own homes. This means the study examined behaviour in the environment where asthma treatment normally takes place.
- Real behaviour: The researchers measured actual attempts to administer medication rather than simply asking parents whether they thought the Funhaler would be useful.
- Short-term study: The Funhaler was used for a relatively short period. Children may become bored with the incentive toys over a longer period and so the findings do not establish whether the effect would continue over many months or years.
Reliability
- Internal Reliability: Is the procedure consistent across the participants in this particular study?
- Standardisation: The researchers used the same two devices, followed the same general procedure, and used the same clearly defined measures of adherence for each child. This increased internal reliability because the procedure and measurement of adherence were consistent across participants.
- Self-report measures: Some information came from parents’ reports. Different parents may have interpreted questions differently or may not have remembered their behaviour accurately. As such, this could reduce internal reliability because the information collected may not have been consistent across parents.
- External Reliability: Can the study be replicated at a different time and with different groups to produce consistent results?
- Easy to replicate: The researchers clearly defined the devices (standard inhaler and Funhaler), measured adherence using clearly defined outcomes, and gave standardised questions to the parents in the questionnaire. This standardisation provides a clear procedure that other researchers could repeat if they wanted to replicate the study.
- Small pilot study: Because the study was small and preliminary, further research would be needed to establish whether the same findings could be reliably reproduced in larger samples.
Ethnocentrism
The study was conducted in Australia and involved a relatively small group of Australian children with asthma.
- Weaknesses:
- Limited cultural representation: The study does not show whether children and parents from different cultures would respond to incentive-based asthma treatment in the same way.
- Different attitudes towards medical treatment: Parents from different cultural backgrounds may have different beliefs about medication, children’s independence, and medical treatment. These factors could affect adherence.
- Australian setting: Because the study was conducted in Australia, the findings should not automatically be assumed to apply in exactly the same way to children from other countries.
However, the basic principle that making a behaviour more rewarding can encourage that behaviour is based on operant conditioning and may apply across different cultures. Further research would be needed to establish whether the Funhaler itself is equally effective in different cultural settings.
Evaluation summary table
| Chaney et al (2004) | |
|---|---|
| Research methods and techniques | Strengths: The field experiment was conducted in the children’s homes and used a repeated measures design, allowing the researchers to compare the same children using both devices. Weaknesses: The sequential use of the devices means that order effects and practice could have influenced the results. |
| Data types | The study produced quantitative data about adherence and successful use of the devices, allowing the conditions to be compared statistically. It also collected qualitative information from parents, providing more detail about their experiences of using the devices. |
| Representativeness and generalisability | The sample was small and consisted of young Australian children, with more boys than girls. This limits how confidently the findings can be generalised to the wider population of children with asthma. However, all participants had asthma and were prescribed the type of medication being investigated, so the sample was relevant to the research question. |
| Ethical issues | Parents provided informed consent and the study investigated children’s normal asthma treatment rather than deliberately withholding necessary medication. However, the participants were very young children, so researchers had an increased responsibility to protect them and ensure participation was appropriate. |
| Validity | The field setting gave the study good ecological validity because children used the devices in their normal home environment. The repeated measures design also strengthened the validity of the findings because the same children used both devices and so differences in adherence were less likely to be caused by individual differences between the children. However, order effects and reliance on parental self-report may reduce internal validity. |
| Reliability | The clearly defined devices, procedures, and measures of adherence improved internal reliability because they made the procedure consistent across all participants. They would also improve external reliability as other researchers can easily replicate them. However, the small pilot sample and use of parent reports mean that further research is needed to establish how reliably the findings can be reproduced. |
| Ethnocentrism | The study involved a small group of Australian children, so it provides limited evidence about whether the Funhaler would be equally effective in other cultures. However, the underlying principle of using positive reinforcement to encourage behaviour may apply across different cultures. |
Relation to developmental psychology more broadly
Chaney et al (2004) contributes to developmental psychology by demonstrating how children’s behaviour can be influenced by the consequences that follow it. The study provides an example of how principles of operant conditioning can be applied to children’s health behaviour.
The study is particularly relevant to developmental psychology because young children often depend on adults to support and encourage behaviours such as taking medication. Making a behaviour more enjoyable may therefore help children develop more consistent patterns of behaviour.
The table below summarises how this study compares with other core studies and evaluates its contribution and current relevance:
| Chaney et al (2004) | |
|---|---|
| How the study relates to developmental psychology | Chaney et al contributes to developmental psychology by demonstrating how the consequences associated with a behaviour can influence children’s behaviour. The study applied the principles of operant conditioning to a real-world health problem and investigated whether making asthma treatment more enjoyable could improve adherence. |
| Comparison with Bandura et al (1961) |
Similarities:
Both studies investigated external influences on children’s behaviour. Both used children as participants and used an experimental method in which an aspect of the children’s environment was manipulated. Both also produced quantitative data that could be compared between conditions. Differences:
Chaney et al investigated operant conditioning by examining whether a more enjoyable asthma device would encourage adherence. Bandura et al investigated observational learning by examining whether children would imitate an adult model. Chaney used a field experiment in the children’s homes, whereas Bandura used a more controlled laboratory experiment. |
| Comparison with Lee et al (1997) |
Similarities:
Both studies investigated children’s behaviour and considered how children’s social environment and experiences can influence behaviour. Both also involved young children and collected information that could be used to compare children’s responses. Differences:
Chaney et al investigated operant conditioning and children’s health behaviour (specifically adherence to asthma treatment). Lee et al investigated moral development (specifically children’s judgements about lying and truth-telling). Lee et al also compared Chinese and Canadian children, allowing the researchers to investigate cultural differences, whereas Chaney et al did not investigate cultural differences. |
| Contribution to understanding diversity |
Individual differences:
The study involved children of different ages and examined differences in how successfully children and their parents used the asthma devices. However, the small sample limited the extent to which individual differences could be investigated. Social and group differences:
The study included both boys and girls, but it did not specifically investigate gender differences in the effectiveness of the Funhaler. The unequal numbers of boys and girls also limit conclusions about differences between the groups. Cross-cultural differences:
The study provides limited evidence about cultural differences because the participants were from Australia. Unlike Lee et al, it did not directly compare children from different cultural groups. |
| Usefulness | Chaney et al is useful because it demonstrates a practical application of operant conditioning to children’s health behaviour. Practical applications include:
|
| Current relevance | Chaney et al is relevant today because adherence to medical treatment is still an important issue in children’s healthcare. The study also demonstrates a broader principle: that children’s behaviour can be influenced by making desirable behaviours more rewarding. This has relevance beyond health contexts (e.g. the design of medicines) to areas such as studying in schools, encouraging healthy habits, and promoting positive behaviour at home. |